

When a doctor asks for better support and better communication, they are not asking you to be friendlier. They are describing a number almost no lab measures: the hours between a case arriving and the first moment somebody with technical knowledge looks at it. Call it time to first QC. In most labs it runs into days, and the doctor only finds out when you call.
Here is what those days look like.
A doctor scans a patient at 4:30 on Monday afternoon and submits the case at 5:15 on his way out. It reaches your queue at 5:16, after your front desk has gone home.
Tuesday morning is the rush. Dozens of scans across six portals, RX forms printed, product codes matched, pans labelled. Monday's case gets booked at standard turnaround and goes onto the shelf.
Thursday afternoon your CAD tech opens the file. The margin on the distal is unclear and there is no shade on the RX. Now somebody has to call the practice.
That margin was unclear on day zero, on Tuesday while the case was being booked, and all day Wednesday while it sat on the shelf. So when you call on Thursday, you are not only reporting a bad scan. You are telling that doctor nobody in your lab looked at their case for three days.
When you think about what causes case delays or remakes in your lab, where do you look? Most labs will chalk it up to bad scans or bad RX information and chalk it up to external factors, but at the end of the day, any delay or remake, has a negative impact on your customers.
A lab that differentiates themselves through support doesn't see that and just say, "well we're doing our job"; they'll take a look at the friction points ask themselves how they can set up guardrails.
Two things at case intake cause most of it. The first is timing. Almost every lab has an unwritten case intake cutoff between 11:30 and 1:00, and most doctors send at the end of their clinical day. The result is that every time a case comes in after that cutoff, it sits for 12 hours before anyone has a look at it, all the while the doctor is under the impression it's being worked on.
The second is who does the looking. In most labs the first real look at a scan is when it gets to CAD/CAM and a technician opens it to start work. That is one of the most expensive people in the building doing one of the cheapest tasks at the latest possible moment. As a result, the case gets sent back to the front desk to call the doctor asking for a rescan days after they had sent the case. Spotting a missing shade or a bad scan takes about a minute. It should not take seventy-two hours.
Neither is visible to your doctors. All they see is when you call.
What a bad scan costs you depends on when it gets found.
Found within minutes, it costs one message. The doctor rescans while the patient is still in the chair, and you are the lab that noticed.
Found the same day, it costs a message and a note on the schedule. The production slot holds.
Found on day two or three, the case comes off the shelf and the slot gets rescheduled. Production absorbs it, and so does the relationship.
Found on day four or later, the case gets pulled, the turnaround promise breaks and the patient's appointment moves. Margin absorbs it, and sometimes the account does.
Same scan. Four different prices.
Remakes are the visible cost. They are not the expensive one. Communication is one of the most common reasons a doctor leaves a lab, and a problem you surface late reads as a lab that was not paying attention.
Five steps, run with the people you already have.
Two timestamps per case. Arrival time is already in every portal. First QC time gets noted by whoever looks at the scan. After ten days, work out the median and your worst case. Most owners are surprised by how much of that time is the case sitting still rather than anybody working on it.
Scans cluster around appointment patterns, usually a late-morning block and a late-afternoon block. Three sweeps timed to that means most cases get seen the same day.
Checking an RX takes about ninety seconds and does not need a CAD tech. Is there a shade, and is it on the RX rather than buried in the notes? Is the margin clear on the prep? Is the opposing arch there? Is this the case the RX describes: right tooth, right product, right doctor? Anything that fails goes into a flagged pile before it reaches the shelf. A trained admin can do this after a week of calibrating against your standards.
Write three standard messages for your most common issues, each with a slot for a screenshot and one clear ask. Store them where whoever does the QC can send them without asking you first. A flag that needs your approval sits there until you are free, and you are never free.
"We can proceed as is, and here is the likely compromise. Or rescan today and we deliver on schedule." One reply closes the loop. An open-ended "there's a problem with your scan" generates three emails and a phone call.
None of this needs software. What software removes is the dependency on somebody having time to do it, which is where the routine breaks.
Downloader pulls cases from your scanner portals continuously, including overnight and weekends. QC reviews the scan and the RX shortly after arrival and flags what your own check looks for. CaseEntry reads the RX, maps your codes, and enters the case into your lab management software ready for production.
Every lab gets the "where's my case" call. A doctor asking it has decided they cannot assume the case is coming.
So count those calls for a month. What does the number tell you about the system underneath it?
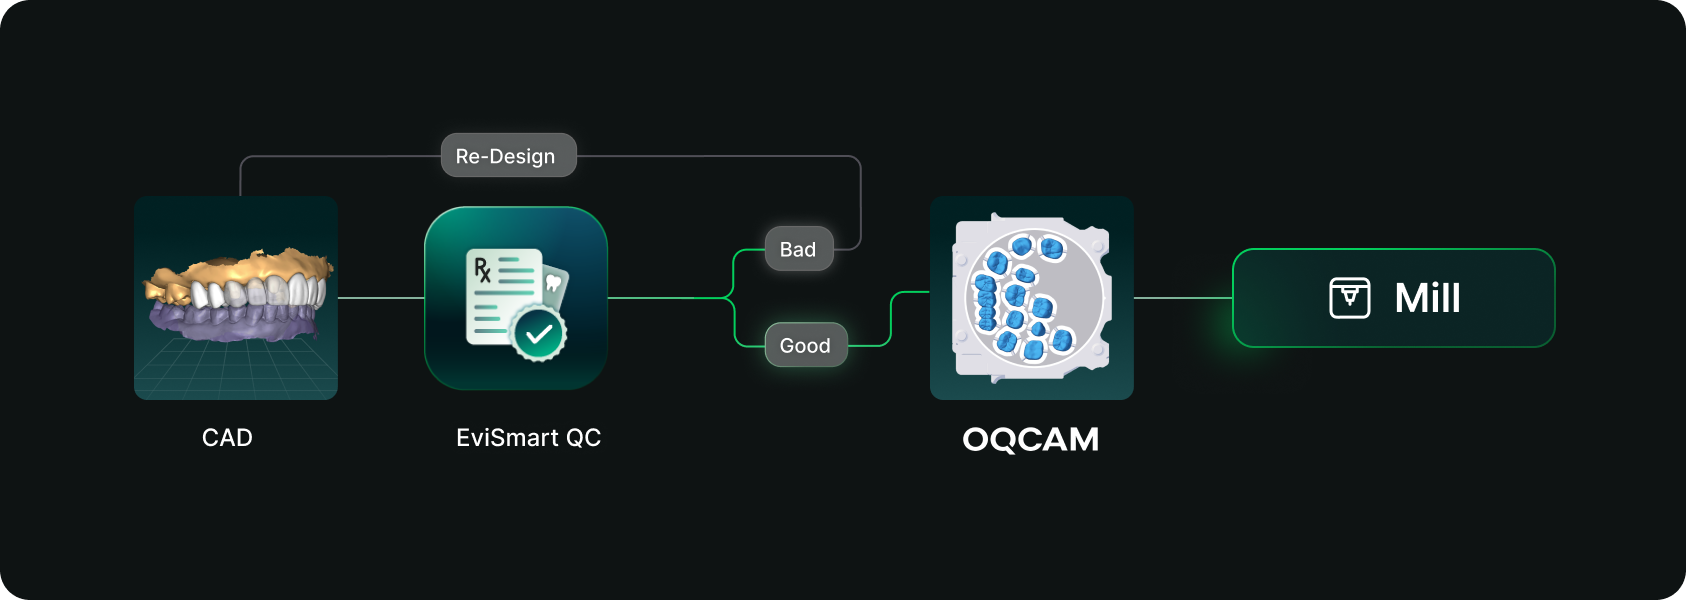
Designs you order from EviSmart arrive in your Oqcam already formatted. Named the way your nesting rules expect, with shade and material attached, and pointed at the machine that case belongs on.
The routing is decided per case. An implant case sends the crown to the mill and puck you cut implant crowns on, and the model to the printer you print models on. Different case types, different machines, chosen automatically rather than by a tech working through a dropdown for every file.
The trigger is QC approval. EviSmart designs your cases your way. The same team works on all your cases and learns what a good case looks like to you. Once your case passes our QC, it triggers a greenlight to send the design directly into your Oqcam account in under a minute.
Once the file arrives in your Oqcam, all your CAD/CAM technicians can review the nested design before starting the mill. That final QC step does not change and is not meant to.
Setup is one session. We connect your Oqcam account and agree where each of your products should go, using the routes and materials you have already built there. Nothing new to create, and you only revisit it if something changes.
Automatic sending only works if you trust what is being sent. Once a case is nested it gets cut, and a design that was not right is wasted material.
You choose what flows. During setup we map only the case types you want moving on their own. Anything unmapped never sends. It waits for you exactly as it does today.
Most labs start narrow. Bread and butter work first, night guards and posterior single units, then widen once they have watched it run for a few weeks. The lab that has been live longest started exactly there and has added case types since.
Your approval stays. This removes the file shuffling between design and CAM. It does not remove your eyes from the build.
For labs outsourcing design work the math gets compelling somewhere north of 30 cases a day into nesting, because that is where the handoff stops being an annoyance and starts being a role.
Not touchless design. Touchless handoff. Every step in that chain that requires judgment should keep requiring judgment, and every step that never did should stop requiring a person.
Nesting requires judgment. Confirming a build requires judgment. Renaming a file so software can read it does not, and never did. It was a workaround that quietly became somebody's job.
Nobody pays you to rename files.




