

We have spent years asking lab owners a simple question: if a dentist can send a scan in seconds, why can it still take a day before that case reaches production? Nobody blames the scanner. The scan arrives fine. The delay sits in what a person has to do after it lands.
Check the portals. Download the case. Print the RX. Book it in the LMS.
Almost every lab says it in roughly those words. What changes is how much is buried inside step one. For one US lab, checking the portals means opening nine separate websites, one after another, because that is where the cases live. 3Shape, iTero, Medit Link, Dentsply, and whatever else the doctor happens to use. Then somebody unzips the folder, matches the doctor and the product code, and types the patient, the shade and the notes into the lab management software. Then somebody else checks whether it got booked at all.
We call it a digital case because the impression is digital. Operationally, it is still an analog relay race.
One lab we work with has a booking cutoff around 11:30 in the morning. After that, the front office is printing scans, closing out the morning's bookings and getting the day's post out.
So a scan that lands at two in the afternoon sits on the server until the next morning.
It was in the building the whole time. It was just not a case yet. That is close to a full working day gone before a tech ever sees it, and it appears nowhere in your turnaround number.
Another owner walked us through cases saved in individual ZIP folders, labeled by day or by scanner, emailed to techs, then imported into design software. Every handoff made sense on its own. Together they add up to something no owner would have designed on purpose.
It usually rests on one person. When that person is off, somebody else works the portals by hand and hopes nothing was missed.
The admin work is not difficult. It is relentless. That makes it easy to postpone, hard to staff, and expensive to grow.
The real problem is not that people are slow. It is that we ask people to carry data between systems that should already be connected.
To grow three to five times, most labs have to hire a line of people to read files.
Production can usually absorb the volume. A UK group shipping around a thousand devices a day told us exactly that: if more cases arrive, the benches handle it. The ceiling is on the admin side, not the technical side.
So every jump in volume means another hire into the role with the worst retention in the building. You pay to advertise it. You pay to train it. Then you pay again when the person leaves and takes the undocumented knowledge with them. Output that depends on headcount is output you rent.
Bad scans and thin prescriptions are not rare. Missing shade. No implant detail. Unclear margins, bubbles, a scan that will not align.
On one call, a lab described poor scans being caught three days after the case entered the building, well after it had moved through design.
By then it costs you twice. The remake eats the margin, and the call to the practice is an apology instead of a heads-up.
Compare that with the lab that tells its doctors it is usually downloading the scan before they go home. Same bad scan. One lab catches it while the clinician can still act. The other calls on Thursday about a Monday case.
The person booking your cases is usually the person who knows your doctors best. They know which practice always forgets the shade, which one calls at four o'clock, and which one is worth chasing.
We asked one owner what that person would do with two or three more hours a day. He answered without pausing: talk to the dentists.
Instead they spend the morning as a file transfer service. Every hour there is an hour not spent on the relationship that decides whether that practice sends cases next month. The work gets done. It gets done by your most valuable front-office person, at the cost of the work only they can do.
A real-time lab does not wait for somebody to pull the case forward. The case keeps moving because nothing in the path requires a person to move data.
The scan is received. The RX is checked. The case is created in the LMS. The product and material are scheduled. The design path is selected. The case is production-ready. The human judgment that remains sits on the decisions that actually need it.
In one lab running the EviSmart Case Intake Assistant, case intake went from hours of admin to roughly 45 seconds of remaining manual touch. Cases that once waited until the next morning now enter production within minutes.
The Case Intake Assistant checks the portals, pulls the case, reads the RX and opens it in the LMS. Nobody logs into nine websites. Nobody retypes a shade. The lab keeps the judgment and gives up the typing.
That is not a faster version of the old process. It is a different way of running the lab.
Trace one real case. Follow it from portal receipt to production-ready. Count every login, download, rename, copy, re-entry, email and wait.
Delete the handoffs that do not need judgment. Connect the decisions that remain to one shared case record.
Measure time-to-production, not just turnaround. The first invisible day is usually the easiest day to win back.
If we followed one digital case through your lab today, where would we find it waiting for a person to move data between systems?
If you already know the answer, that is the case to trace this week.
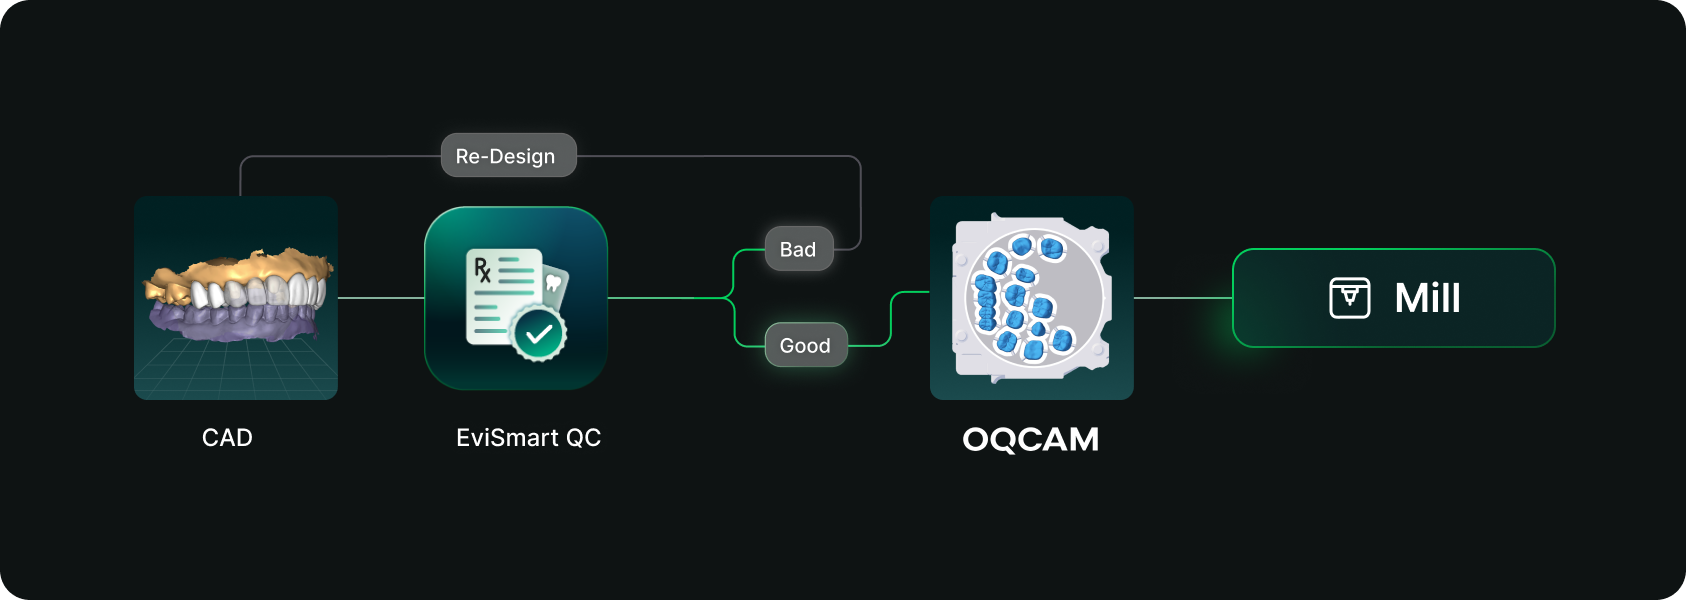
Designs you order from EviSmart arrive in your Oqcam already formatted. Named the way your nesting rules expect, with shade and material attached, and pointed at the machine that case belongs on.
The routing is decided per case. An implant case sends the crown to the mill and puck you cut implant crowns on, and the model to the printer you print models on. Different case types, different machines, chosen automatically rather than by a tech working through a dropdown for every file.
The trigger is QC approval. EviSmart designs your cases your way. The same team works on all your cases and learns what a good case looks like to you. Once your case passes our QC, it triggers a greenlight to send the design directly into your Oqcam account in under a minute.
Once the file arrives in your Oqcam, all your CAD/CAM technicians can review the nested design before starting the mill. That final QC step does not change and is not meant to.
Setup is one session. We connect your Oqcam account and agree where each of your products should go, using the routes and materials you have already built there. Nothing new to create, and you only revisit it if something changes.
Automatic sending only works if you trust what is being sent. Once a case is nested it gets cut, and a design that was not right is wasted material.
You choose what flows. During setup we map only the case types you want moving on their own. Anything unmapped never sends. It waits for you exactly as it does today.
Most labs start narrow. Bread and butter work first, night guards and posterior single units, then widen once they have watched it run for a few weeks. The lab that has been live longest started exactly there and has added case types since.
Your approval stays. This removes the file shuffling between design and CAM. It does not remove your eyes from the build.
For labs outsourcing design work the math gets compelling somewhere north of 30 cases a day into nesting, because that is where the handoff stops being an annoyance and starts being a role.
Not touchless design. Touchless handoff. Every step in that chain that requires judgment should keep requiring judgment, and every step that never did should stop requiring a person.
Nesting requires judgment. Confirming a build requires judgment. Renaming a file so software can read it does not, and never did. It was a workaround that quietly became somebody's job.
Nobody pays you to rename files.




